World Health Organization Expresses Deep Regret Over United States Intention to Withdraw From the Global Public Health Body

The World Health Organization (WHO) has formally expressed profound regret following the announcement that the United States of America intends to withdraw from the international public health agency. This decision marks a significant turning point in modern multilateral diplomacy and global health governance, threatening to disrupt decades of collaborative biomedical research, emergency response coordination, and disease eradication initiatives. As a founding member that helped draft the WHO constitution in 1948, the United States has historically served as both the primary financial benefactor and a strategic intellectual leader within the organization. The impending departure raises urgent questions regarding the future stability of global health security, the financing of vital eradication campaigns, and the geopolitical architecture designed to combat transnational pandemics.
Global public health experts, international relations scholars, and Member States are closely evaluating the profound implications of this announcement. The WHO, headquartered in Geneva, Switzerland, coordinates responses to humanitarian health emergencies, establishes international sanitary regulations, and provides technical assistance to resource-limited nations. The withdrawal of Washington not only alters the organization’s budgetary framework but also challenges the foundational premise of collective global health security—the understanding that pathogens respect no borders and that localized outbreaks demand coordinated international interventions.
Historical Foundations and Seven Decades of Partnership
The relationship between the United States and the World Health Organization dates back to the aftermath of the Second World War. On July 22, 1946, representatives from 61 nations, including the United States, signed the WHO Constitution in New York. The agency officially came into existence on April 7, 1948, after the requisite number of ratifications by Member States. From its inception, the United States played an indispensable role in shaping the organization’s governance, scientific priorities, and operational strategies.
Throughout the Cold War and into the contemporary era, American scientists, public health administrators, and policymakers have worked alongside international counterparts within the WHO framework. This partnership yielded some of the greatest triumphs in modern medical history. Most notably, the global campaign to eradicate smallpox—culminating in the official declaration of eradication in 1980—was heavily spearheaded by American financial contributions, epidemiological expertise, and logistical support through the WHO. Furthermore, joint efforts by the United States and the WHO have brought the world to the brink of eradicating poliomyelitis, reducing wild poliovirus endemic countries to just a handful globally through the Global Polio Eradication Initiative.
American academic and research institutions, including the Centers for Disease Control and Prevention (CDC) and the National Institutes of Health (NIH), have long maintained official designations as WHO Collaborating Centres. These designations facilitated a seamless exchange of data, surveillance reports, and laboratory specimens, directly protecting the American domestic population from emerging infectious threats such as influenza, Ebola, Zika, and multi-drug resistant pathogens.
Chronology of Institutional Reforms and Evolving Tensions
Over the past seven years, the WHO has implemented the most comprehensive set of administrative and operational reforms in its history. These transformations were specifically designed to enhance institutional accountability, maximize cost-effectiveness, and deliver measurable impacts in low- and middle-income countries. Member States, including the United States, participated actively in these governance reviews, pushing for greater fiscal transparency and more targeted emergency response mechanisms following criticisms faced during the 2014–2016 West African Ebola epidemic.
Despite these modernization efforts, geopolitical friction periodically strained the relationship between Washington and Geneva. The tension intensified dramatically during successive global health crises, where domestic political considerations in the United States occasionally clashed with the multilateral consensus required to manage international outbreaks. Debates over intellectual property rights, vaccine equity, drug pricing transparency, and the origins of novel pathogens further complicated diplomatic engagements.
The formal notification of withdrawal initiates a complex legal and administrative process outlined within the WHO Constitution and United States legislative requirements. Typically, such a withdrawal involves a designated notice period, the settlement of outstanding financial obligations, and protracted negotiations regarding the reassignment of technical personnel and the future status of collaborative research agreements.
Financial Architecture and Operational Impact
The financial implications of a potential U.S. withdrawal are vast and multifaceted. The WHO operates on a biennial budget financed through two primary mechanisms: assessed contributions (mandatory dues calculated based on a country’s wealth and population) and voluntary contributions (earmarked funds provided by Member States, philanthropic foundations, and private entities).
Historically, the United States has been the single largest contributor to the WHO budget. In recent funding cycles, total U.S. contributions—comprising both assessed dues and substantial voluntary donations directed toward specific programs like polio eradication, health emergencies, and maternal and child health—have accounted for hundreds of millions of dollars annually. A permanent cessation of these funds would create an immediate budgetary deficit, forcing the organization to scale back operations in fragile states, reduce technical assistance, and potentially compromise global disease surveillance networks.
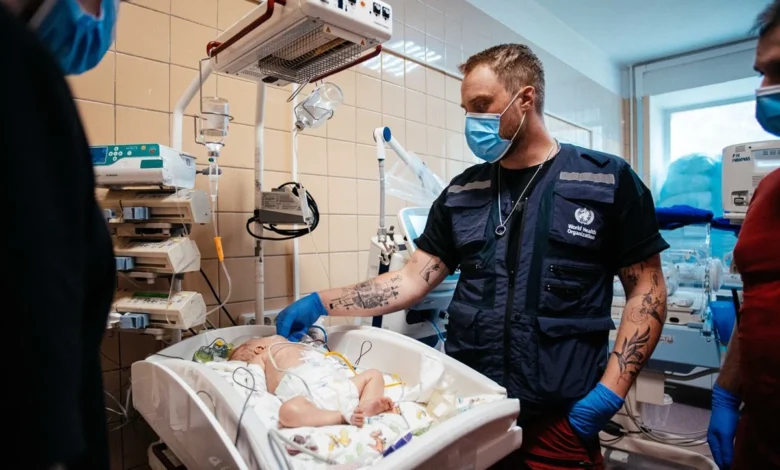
Beyond direct budgetary support, the withdrawal threatens operational synergy on the ground. WHO operations frequently rely on the deployment of elite epidemiologists, virologists, and logisticians from American public health agencies. Without formal institutional integration, sharing real-time genomic sequencing data, epidemiological intelligence, and clinical trial results could become significantly more bureaucratized and delayed, increasing the vulnerability of all nations to rapid-spreading pathogens.
International Reactions and Diplomatic Appeals
The announcement has triggered widespread diplomatic anxiety across the international community. Representatives from European, Asian, African, and Latin American Member States have voiced deep concern over the fragmentation of global health governance at a time when transnational challenges—including antimicrobial resistance, climate-sensitive vector-borne diseases, and the constant threat of a novel pandemic influenza—demand unprecedented international cooperation.
Public health advocates and nongovernmental organizations have similarly condemned the move, emphasizing that disease eradication and health system strengthening cannot be achieved through isolated national strategies. Analysts note that while domestic political imperatives often drive nations to reevaluate multilateral commitments, the tangible benefits of a centralized, universally recognized technical health authority heavily outweigh the structural frustrations of international bureaucracy.
In its official statements, the WHO leadership has maintained a conciliatory and constructive tone. Emphasizing the seven-decade history of shared achievements, executive officials have formally urged the United States government to reconsider its position. The organization has underscored its readiness to engage in substantive, open dialogues to address American concerns, preserve the historic partnership, and ensure that the health and well-being of millions of vulnerable people worldwide are not compromised by geopolitical divergence.
Future Outlook and Broader Implications for Multilateralism
The decision of the United States to withdraw from the World Health Organization carries ramifications that extend far beyond public health, touching upon the broader future of the postwar multilateral order. As international institutions face mounting skepticism and populist pressures globally, the departure of a founding superpower weakens the institutional cohesion designed to manage transnational crises collaboratively.
If the withdrawal proceeds to its final conclusion, the global health landscape will likely undergo a fundamental realignment. Other major economies and philanthropic entities may be called upon to bridge the resulting financial gap, though duplicating the unique technical authority, normative standard-setting power, and global convening capacity of the WHO remains a formidable challenge. Regional health security architectures could also gain prominence, leading to a more decentralized and potentially fragmented approach to international disease control.
For the United States, disengagement from the WHO risks isolating American scientific institutions from global epidemiological data streams, potentially diminishing the country’s early-warning capabilities against emerging biological threats. Conversely, proponents of the withdrawal argue that bilateral assistance frameworks and independent domestic health protections offer greater accountability and alignment with national strategic interests.
As the diplomatic process unfolds, the international community watches closely to see whether a compromise can be reached. The ultimate resolution will depend heavily on upcoming legislative debates, executive branch reviews, and the willingness of both Geneva and Washington to negotiate structural reforms that satisfy American expectations while preserving the integrity and universal mandate of the global health body.